Dr. Jennifer Hoffmann - Pediatric Mental Health and Droperidol (8/9/2022)
Dr. Jennifer Hoffmann reviewed 6 studies of droperidol for severe agitation in children, covering 198 patients. The drug sedated kids in about 14 minutes with few serious side effects, though evidence quality was low. Her hospital added it to their protocol but switched back to olanzapine when supply ran short.
Questions this video answers
Six studies.
198 patients representing 241 droperidol administration episodes.
Median 14 minutes (IQR 10–20; range 3–85 minutes in one study).
Mean ~58.5 minutes (approximately ±30 minutes).
21% in one study (n=102) and 8% in another study (n=26).
Chapters
And physical restraints varies by EMS system, EMS and system characteristics. This tells us that.
The significant regional variation suggests the need for further standardization to reduce restrictive interventions, and it also highlights the need for national education and aligning the alignment of protocols for behavioral health.
And then we're going to have Dr. Hoffman speak about our diperidol study. We'll take questions about these studies at the end.
So as background we know that acute agitation by children with mental and behavioral health conditions poses significant patient and staff safety risks, such as the risk of injury. Verbal de escalation is always preferred when possible, and oral medication is preferred when over parenteral medications such as intramuscular medication, but parenteral medications are used when necessary for safety. However, pediatric data on medication effectiveness and safety is limited for the medications commonly used for this purpose.
So the aim of this study was to perform a systematic review of the effectiveness and safety of droperidol for the management of acute severe agitation in children in acute care settings.
In terms of article eligibility. In order to be included in the review, the article had to review the effectiveness or safety outcomes for intramuscular droperidol. It had to be administered for acute agitation in youth under 21 years old, and this had to occur in an acute care setting such as the pre hospital ED or inpatient medical or psychiatric unit. And we utilized a search strategy developed by a professional librarian.
This flow diagram shows the process of article selection. The literature search strategy ultimately started with up to 1000 articles. We screened the titles and abstracts, reviewed the full text of about 100, and ultimately only six articles met the eligibility criteria for this study.
So the six articles that we found on Droper et al included two in the pre hospital setting, one in the ED, and three in the inpatient hospital setting. Importantly, none of the studies compared droperidol to another medication commonly used for agitation such as haloperidol, olanzapine, or diphenhydramine. There also were no randomized controlled trials, only one prospective observational trial. Three of the studies were retrospective and two were case reports of the studies. In total, there were 198 patients representing 241 medication administration episodes of droperidol.
This table summarizes the results from the six different studies. The first column just shows there's significant variation in the dosing protocols that were utilized across the studies with varying weight based dosing as well as ranges in the maximum dose. For adult sized patients, the maximum dose ranged from 3.1 milligrams, but the more common maximum doses were 5 or 10 milligrams and I'll summarize the effectiveness and safety outcomes on the next slides.
So in terms of effectiveness outcomes, time to sedation was relatively short. One study reported a range of three to 15 minutes, another study reported 10 to 15 minutes, and a third study reported a median time to sedation of 14 minutes, with an interquartile range of 10 to 20 and an overall range of 3 to 85, suggesting that doperidol may have a shorter onset of action than other commonly used medications in terms of depth of sedation. One study reported a failure to sedate in only 1 out of 102 cases, and however, this did include some patients who received multiple doses in order to achieve adequate sedation. A second study reported that 86.6% of cases resulted in effective sedation. The duration of sedation was reported in only one study with a mean duration of 58.5 minutes plus or minus about half an hour, suggesting that doperidol may have a shorter duration of action than some of the other medications we commonly use, which could be helpful in that the child is not sedated for a long duration of time and they're able to participate meaningfully in their psychiatric assessment after they arrive to the ED. There were some children who needed a second dose of medication. This occurred in 21% of 102 cases in one study and in 8% of 26 cases in another study.
In terms of safety outcomes, the most important one that we looked at was QTC prolongation. Doperidol does carry a boxed warning from the FDA due to QT prolongation that has been reported primarily based on some adverse events that occurred outside the country when used in doses much higher than are typically used in the United States. But in our pediatric study we only found one reported case of QTC prolongation and that occurred in a patient who had an ingestion, so we don't know if their QT prolongation was related to the droperidol or related to a medication they may have taken during the ingestion. Their QTC was 505 after receiving a 10 milligram dose. Other reported safety outcomes included hypotension. In six cases, four resolved without intervention. One patient was given IV fluids upon which the hypotension resolved, and in one study it was not specific specified whether intervention was needed. There was one patient with alcohol intoxication who had respiratory depression with an oxygen saturation of 88% that resolved with supplemental oxygen, again unclear as to whether that was related to the droperidol versus the alcohol intoxication and the most common adverse effect was a dystonic reaction which is a sustained involuntary contraction of muscles that that sometimes can be mistaken for a seizure. This occurred in five cases and all of these cases improved with administration of diphenhydramine or benztropine, which are the recommended agents for treatment.
So we performed a risk of bias assessment on these six studies using a tool called the Risk of Bias in Non Randomized studies of Interventions, also known as the Robin's Eye tool. This was developed by the Cochrane Methods group and you can see the results in the chart on the right. The red indicate areas of the studies that had moderate to serious risk of bias and the right hand gray column represents the overall risk of bias in each of the six studies. So all of the studies were unblinded and observational and none of them adjusted for confounders such as age or sex. So therefore it is somewhat difficult to interpret the results and many of these results may be low quality.
So in summary, we found that troperidol seems to have a reasonable effectiveness and safety profile. Most patients were sedated within 15 minutes and remained so for about one hour, which is favorable relative to some other medications currently in use that have both a longer onset of action and a longer duration of action which may preclude patients from participating in their psychiatric assessment. Up to one in five may need a second dose and adverse effects are relatively rare with a similar profile to other available medications. And go to the next slide.
So the results do mirror findings from adult studies which have much, much larger numbers of patients. You can Some of the adult studies have had up to 16,000 patients and there also have been randomized controlled trials conducted in adults, whereas there have not been any in children. And some of those randomized controlled trials in adults showed one showed superiority of a droperidol midazolam combination over either droperidol or Lanzapina single agents. Another showed superiority of droperidol over lorazepam or ziprazidone and it also caused less respiratory depression. There was one other study I didn't put on this slide that did suggest doperidol has a higher chance of extrapyramidal side effects, meaning dystonic reactions relative to olanzapine. Overall, pediatric data is limited and low in quality and verbal de escalation is always preferred. Next slide.
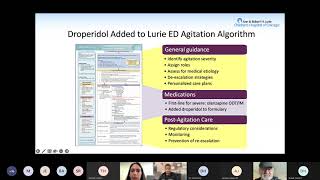
So we did add doperidol to our local ED agitation algorithm for care within our ed. This is what our algorithm looks like. It provides general guidance on agitation care, suggested medication dosing and post agitation care considerations. So we were using it for about six months, but then more recently there's been a supply shortage that's limited our ability to continue to use it. So we've gone back to Olanzapine as first line in our ad currently. Next slide.
So we have lots of ideas for next steps for our research group and we'd love to hear from you guys. Which of these questions are important for us to tackle and answer next? Some of our ideas include comparing the effectiveness of intramuscular medications against each other in children, validating a standardized numeric rating score for agitation in children, developing a tool to select which children may be safe to divert from medical EDs to freestanding psychiatric facilities, developing brief videos or simulation training for pre hospital personnel on verbal de escalation, or developing personalized care plans for children with recurrent agitation.
Next slide.
So overall, we'd love to hear from you on what are the important next study questions for us to answer? What tools, resources or educational modules are desired by EMS personnel and what's most helpful or challenging when caring for these children? These are email addresses and we'd be happy to answer questions.
Okay, well, thank you very much. Can you hear me okay right now?
Yep.
Okay, good. Well, thanks a lot. This is actually really great because it's echoing what we're looking at on a larger level with the jurisdictional medical directors from the large cities and particularly working with troperidol. And so this has been fantastic and it's really congruent with where we're going. And thanks for all the homework you did on this because it's tough looking at studies in children, as you know, because the numbers, et cetera. But this has been very good. So thank you. So I want to first of all, before I go any further, for those of you who collect the CME here, our CME code for today, and if someone can put it in the chat for me is 1-5277-15277. So I want to pitch it to the floor before I have to get off, which will be in about five minutes. And anybody have any questions or comments to make?
I'm interested in the treatment of the extrapyramidal reactions. How did you approach it?
So the two agents that are typically used for extrapyramidal reactions are diphenhydramine or Benz terpene. Diphenhydramine is much more widely available, so that's what I'd recommend as first line. And in all the cases that we found Reported in the literature, they resolved after administration of diphenhydramine.
Thank you. Yeah, and that's pretty much what we've been doing. And that sounds fantastic. And I don't think it's not that common. It's just they like to always make sure we cover that, so. Good. Any other questions or comments? Yeah. Dr. Naik, question for you. Mike Lozano, University of South Florida. You had factors such as west versus south in terms of increased odds of use of restraint. Were there any other factors? So you mentioned age, but location, neighborhood, sex, race, anything else that would.
I figured that this odds. I figured this might be a question. So I. In our next slides. Here we go.
So.
We did look at a few other ones. What I highlighted in the slideshow was essentially just a small amount. So you can see age here. So in this table you can see the encounter characteristic on the left, the adjusted odds ratio for sedatives. And like the second column, the third column is restraint use and then the last column is any intervention. And so age, you can see for restraint use, you can see that the 6T11 age group has a higher odds as well as a higher odds for any intervention. So that's what I would highlight for age for gender across the board. Male, Male, if you compare male to females, have a relatively high higher odds ratio of receiving sedative medications or restraint use. And then with regard to the type of region, whether they're urban, suburban, rural, or in the wilderness.
When you compare them all to the urban category, they're all relatively lower.
There's more. And so when you also take a look at EMS regions, your primary impression or alcohol or drug use for the EMS regions, this is where we derived our data. You can see there in the middle for the restraint use.
And then the sedative use over there with the 1.51 in the Western plains, I thought that the primary impressions were also quite interesting but logical when you compare them to everything, to suicide or self injury, you do see increases across the board and the disruptiveness, substance related use or other primary impressions and alcohol or drug use, again is more logical with regard to that increasing.
Then this is what we highlighted at the top here with regard to kids with developmental communication or physical disabilities receiving sedative medications or restraints. And then I believe the last part of your question with regard to EMS systems, you can see that.
You have restraints being, if you compare to the fire department, you have restraints being used more in government, non fire and private, non hospital groups as well. Yeah.
Yeah.
So I hope that These slides better answer your question. There was a little bit more that we looked at.
Great, thank you. And it wasn't a planted question. It's just really good. I know.
This is, this is great.
Yeah, it's definitely. This is usually not a plant based group. Okay, so then you have your emails up there in case anybody wants to talk to you further. Any other questions or comments.
If not. Yeah, I guess we can go ahead and let you guys go because we have to switch over to another show and then you're going to take care of that one, right? In this case, Angus, you'll be able to do the switch the switch over. I hope so. Okay, that's good. Well, that's it. Now Jennifer and, and Shaw, thank you so much, so much for your time today and give us in for the work that you're doing as well. So next time up, I'm up in Chicago, we'll go hit Valari's with you. So it sounds good. Okay, so thank you so much then for all your anybody else going, going, gone here. If we don't have another question or.
Comment, thanks for having us and please send us any ideas that you want us to carry out or let us know how we can be of help.
Okay, well, thank you, Ken. All right, close it off and I'm going to switch over to the Eagle side. Okay. So thanks a lot.
And Again, our, our CME for today was 15277. 15277. This is Rocky Short signing up.
All right, any other discussion or issues around Florida.
More from Peter




Melissa Olen MSN, FPN-C, CCRN: Sudden Cardiac Arrest Training in Schools (Project ADAM) 4/25/25



Pediatric Hospital Readiness: How Teamwork & CPR Metrics Drive Better Outcomes



Chelsea Kadish, MD & Kyle Goodknight, EMT-P, RT: Pediatric CPAP in EMS (3/14/25)