DocuFast Eval magic 33
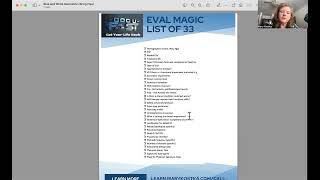
Mary Kostka walks through 33 essential elements for occupational therapy evaluation reports, from demographics and diagnoses to measurable functional goals and skilled OT justification. She covers what makes therapy necessary, safety concerns, treatment codes, and frequency recommendations. DocuFast templates cut eval writeups to 15 minutes and save clinics $30,000 to $100,000 yearly.
Questions this video answers
33
15 years
About 15 minutes
About 5 minutes
About 3 minutes
Foreign everybody. Mary Koska here and I'm going to share with you my my docufast eval magic list of 33. So these are the things that I like to make sure that are in my evaluation reports. So I'm going to start off with some of it's just pretty obvious like your demographics and some insurance companies also like you to have the membership ID in there as well. Primary care provider, the medical diagnosis, you want to make sure you put the number and the letters that go with that. Not just the name and the treatment diagnosis as well. We use a lot of coordination, weakness, unspecified disorder of the nervous system. Those are common ones that we use for treatment diagnosis. And you want to include if there has been a pre exam form that includes the medical history. This is really important because by noting that you've obtained it and you have it, you don't have to regurgitate it in your report. So I just pull out the most significant aspects from the pre exam and medical history. I don't restate the whole thing and of course the date. I want to say yes or no if they're appropriate for therapy. And it's really important to identify if there's a functional impairment in what it is. I think it's really easy to get sidetracked if you're using standardized evals to not really address the what's the functional concern. So I'm very function oriented. My evals are more clinical observation based and function oriented. I do do the SPM and I will throw in something like else if I need to first for score or whatever. But I'm really trying to address the functional impairment and the underlying concerns. So I like to get a very clear measurable functional impairment goal from the parents. So it might be something like that they can take their child to a grocery store without a meltdown. It might be that they're not physically aggressive for a month. It might be that they're able to stay in school because the parent keeps getting having to miss work because they have to keep picking them up. Something very, very clear and measurable is important to have there secondary impairments. I will put the other concerns that the parents have, the other things that they've noted in the intake and then also the things other things that I observed during the eval. And the concern level is kind of like a pain scale of 1 to 10 and so I like it's really fun to do that because it's just a nice easy way to compare beginning to end at discharge. So typically our parents will be at a 7, 8, 9, 10 concern when they bring their child and they'll be at a 0, 1, 2 or 3 when they leave. Severity of the condition, mild, moderate, severe. You do want to see if you think the condition will improve and I do a lot of treatment in my evals because pretty much I can't get much from the child unless I'm treat treating them to get it. So and with billing treatment you want to show that you did some treatment too. So pre test activity justification results. So for me I would do typically something to help them sit and focus more. So I might do something like the Wilburger depressure protocol and note that they couldn't sit down at all or they could sit for a minute and afterwards they could sit maybe for five minutes and then, then I'm able to get the other things done like ocular, motor, stereo agnosis or the things that require a little bit more sitting and focusing. So you like to say how they did in the beginning and then the other thing is really it just helps justify that what we're going to do is probably going to benefit the child and then you want to say there's a chance that the condition could get worse. For example, if they have a progressive illness and will the therapy improve their functional skills. Again, insurance is more focused on function than anything else. Safety concern impression. I almost always am able to put something here that really helps with medical necessity. Typically a lot of my kids hurt themselves or other people so due to coordination problems. So yeah something in there about that or if they're just aggressive, any anything you know if they tend to fall and trip often, just whatever the safety concern might be and then the exam type performed. So you got your high, medium and low there. Next step orders. You're going to say if you're recommending therapy limiting factors to success. This is where I'm going to put the things that I found most significant from the intake and medical history. It's things that I think could impact our progress. So say they're a foster adopt child but they had been previously in five homes or if they have multiple other diagnoses, just anything, medication side effects, just anything I think is pertinent there what's causing the functional impairment. That is really my clinical assessment of from all my testing what I think the main issues are. So it might be primitive reflexes or core or per session, vestibular, tactile, just whatever I think the main issues are. That's where I'm going to put that. And then how severe I think it is justification for skilled ot. It's really important to have a statement here. I have a pretty, pretty nice set statement that I use that really explains what I'm going to be doing differently than if it was a caregiver. And mainly, you know, they haven't, they haven't got these skills yet and they need adaptations or grading of the activity, they need specialized assist, just anything like that. And of course I want to say what their potential is and recommendations here. I would also put, if I'm recommending other services or other types of evaluations, long term goals, short term goals, procedures intended, this where you're going to put your 97530 or whatever code you're using to bill and you want to list all of them that you think you might possibly use and then your frequency. I used to be very vague about this, but I've learned that the more specific the better. So you really want to be clear like one time a week for 60 minutes, for a duration of 40 sessions or whatever it is that you think. And, and then you're going to put your billing codes in there and sign it, date it, pitch title and have a place for the physician. So those are the things that I think are most important to have in an eval. And I've had my private practice 15 years now and I have anything that I've ever had scrutinized appeals that I've done, anything, I've won them all. And so I'm very comfortable and confident with how important all of these things are to have in, in your report. And if you'd like to learn more, I can hop on a call with you. You can learn more at merry learn maricoska.com forward/call. It's there at the bottom there. I think there'll be a link on here too. And, and you can have a, a 20 minute free little consult with me and I can help you give me any tips that, that I'm thinking of that might help you. And if you want to learn more about if Docufast is a really good fit for your clinic, I'm really selective who I sell it to. It is a higher ticket item. And so it's really important to me that it's, that it's a perfect fit for the clinic, that it's really going to make a huge difference. And so I really like to talk to people first before letting them have it. And, and so we can do that. And I can give you a sneak peek into it as well. I. It's the culmination of everything that I do in my clinic, from intake to discharge. And there's it's. It's really a suite of templates and tools and videos and strategies and basically everything that I do in my clinic. And we have our eval writeups down to 15 minutes and re our pragues revals are like 5 minutes to do and our notes are usually about 3 minutes. So we've got this down and happy to help other clinics really cut their time in half or better. And then that way you can use that money for that you're paying for clinicians to document to either see more kids or just be able to put that into your staff into paying yourself back for what you've invested just however you want to use that money. But typically clinics save anywhere between 30 and $100,000 a year by cutting their time in half. It really depends on how much time they're spending now, but that is a typical range. So I would be more than happy to help you. So hope to see you on a call soon. Bye.










