Science and Technology: Tiny Health June Practitioner Office Hours

Kim and Emily Serta explain why Tiny Health uses shotgun metagenomic sequencing instead of cheaper alternatives like 16S rRNA. It captures the full microbial community down to strain level and quantifies functional genes like butyrate production. The panel covers sample handling, age-specific reference ranges, and how to interpret results when signal is low.
Chapters
Getting started on time today, everyone, because we have a lot, a lot of fantastic content to get through. So thank you for joining us today for our June Office Hours for Tiny Health. If you are new here, welcome, we're so happy to see you. And if you are a returning guest, then welcome back. Gonna get a lot of great content today. We have a packed schedule. Uh, our topic today for doing Office Hours is Superior Science and Technology. We're going to be really diving in in detail to the concept of the technology behind Tiny Health and really what sets our tests apart. And my name is Shalese. I'll be moderating our Q&A today. We're having a little bit of a different format. And so what's going to be happening instead of a, you know, classic presentation where we do some education and have Q&A afterwards, we're actually going to have a little panel here with Emily, and Kim, Emily from our clinical success team, and Kim from our science team. I'll be introducing both of them in a second. We have a couple announcements to get started, and then we're gonna get going into our topics. We have some prepared questions. We also, if you registered for this office hours, you probably saw that this was the first time that we had the option to, oh, and Christine has joined us as well. Thank you, Christine.
Say hi.
You've probably saw that this was the first opportunity to submit some questions. To be answered. So we have some prepared questions, we have some submitted questions, then we're going to leave some time also ideally for some live Q&A. That will be our goal. If you have questions while we're going through the presentation, please feel free to type them into the chat. Christine's going to be hanging out in there to help answer questions, and then we'll be able to get to any sort of lingering questions that are prevalent— relevant— relevant, there we go, to the topic and go through those at the end. So let's get into it, everybody. Our first question we always get is, is office hours recorded and where can I access it? So yes, the answer is office hours are always recorded. You can always access the recording later on in our practitioner resource page. Uh, you can log in to view it and you can access the slide deck as well. So today, uh, we're just going to be doing the live Q&A with Emily and Kim, so we don't have as formal of a deck. We're going to be referencing some of the technology deck slides though, which is already actually in our practitioner resources drive. So if you've taken a look at that or have not, notice that's in there, then that is the deck that we're gonna be referencing today. All right, so this is where— this is what it looks like when you pull it up, our poweredbytinyhealth.com/resources. So that's where you'll be able to access this information later on. We're going to start off with a quick little poll. Let me pull it up here. All right, if you could please take a few moments to complete our poll, we would really appreciate it. We love to see who is here for the first time, who is coming back to join us, and how you heard about Tiny Health. So if you could, we'll leave that up for just like a minute and a half. Because we do have a lot to go through today, so I don't want to spend too much time on our poll, but we really want to just capture that information if possible. So go ahead and fill that out. It should have popped up on your screen and you can just click on it and then exit out. All right, while we're waiting for people to complete that, I'll do a quick little introduction of our panelists today. So as I said, my name is Shalese, I'm the Clinical Success Manager here at Tiny Health. I'm going to be interviewing Emily Serta, one of our microbiome specialists and our veteran here on the clinical team. She's been here the longest. And then also Kim. And Kim, you actually, you just got a new title change, correct?
I'm Chief Science Officer.
Yeah, Chief Science Officer. Kim has also been here for, you know, since the beginning of Tiny Health, pretty much. And so she is our expert today when it comes to Tiny Health technology. She has her hands in everything behind the scenes and also what you see as the practitioner when it comes to how the science and the technology is represented on the Tiny Health Test. So, so excited to have her here as our guest today. Very, very special. All right. We're going to end our poll. Thank everybody for those who answered. I truly appreciate it. Finish up the questions. I'm going to end it. All right. Thank you so much. All right. Let's move on. We got just a couple announcements. We have our little disclaimer here. You know, this is educational for practitioners. This information is not intended to, you know, diagnose, treat disease. This is our educational webinar content, so please keep that in mind as we're talking about the information. And then we also, you know, as you are attending our events and registering for them, you might be opting into certain educational emails and promotions from our partners. So please keep an eye out for those. But if that's not your thing, feel free to unsubscribe from them. If you have not met with any of our, our, sorry, account manager team, sorry guys, my brain is not connecting to my mouth well today. So our account manager team is here to support you. If you are new to Tiny Health, they would love to meet with you. And give you an awesome $50 off coupon for a first-time order. So Christine is part of that team, and she is here today in the chat. If you have questions for her or want to meet with one of our team members, please let us know. We would love to schedule a call with you. And if you have run a test and taken advantage of our clinical team members that can support you, our microbiome specialists, in interpreting those test results and helping apply them to your patient, then you probably met one of us, one of our team members. Kathleen, Maya, Emily, Lisa, or myself might have met with you to review, and Danielle too on occasion might have met with you to review a test. And so this is our clinical team. Please take advantage of us if you're needing support in learning how to utilize and interpret our Tiny Health tests. Here's some practitioner love that I love. I like to just, uh, we really do appreciate and love to collect feedback from our practitioners. So every time you have a meeting with us, we do send a little survey afterwards. You've probably seen that if you've met with us, but we just, we so appreciate your feedback and we are always working to improve the test, our support, our resources based off of your feedback. So thank you. Here's some just ways you can connect with Tiny Health this month. We're going to be, we are supporting NCIMS in Asheville, North Carolina. And then Danielle is doing a webinar with Learn Skin on June 16th. If you would like to attend that, you can go to their website and register. All right, let's get into it. Today we have Superior Science and Technology. As I mentioned, we're doing a live interview with guests. And so it's very exciting today. Emily and Kim are here. We will be diving right into some questions, and then our goal is to leave some time at the end for some live Q&A. So these are our learning objectives for today, talking about shotgun metagenomics and the difference between other types of technology out there when it comes to stool testing, reading reports with confidence. Emily's gonna help support and explain So, like, the clinical application of some of these technology aspects that we're diving into today, it's gonna get pretty technical. So make sure you, if you wanna take some notes, you can. And then also understanding the validity of different microbiome markers, what they actually mean in their context, understanding the difference between functional gene potential and taxonomic composition in the gut microbiome. So those are our topics for today. Let's get started. And Kim, if you would like to, you can feel free to share your screen now or whenever you're ready, but we're gonna get started with questions. Ready, ladies? Okay, let's go. All right, so we're gonna start off with one of the most common questions that we get when it comes to practitioners who are new to Tiny Health, and that is, what is shotgun metagenomic sequencing? What's the benefit of utilizing that and how does it compare to other types of technology on the market such as qPCR culture tests?
Cam? Yeah, big question. We'll probably take a while answering it, but let's start with the core. What is shotgun metagenomics? So our test uses shotgun metagenomics. It's the gold standard in microbiome research nowadays. It's, it's what's kind of give us the most complete picture. But what actually is it doing? So you send in a tiny swab of stool. That stool hits our lab, goes through QC, and we extract all the DNA that's present in it. Now, this is really important. We're not just looking at bacteria here. We're looking at the fungi that are present, any other general microbes. So the archaea, the everything that's present in that sample is, is sequenced and it's chopped up into tiny little pieces. That's why we call it shotgun metagenomics. So you end up with all of these small fragments of DNA that all go through the sequencer at once. And we sequence all of it. So what we're getting here from the shotgun metagenomics approach is we're getting all of the species, all of the taxa that are present, and we can characterize it all the way down to the strain level for many cases. We're also getting all the functional genes. So we'll see fragments of butyrate-producing genes. We'll see, we'll see short-chain fatty acid producers, cellulose degraders. We'll see all of these different genes that we also put into the report. So for, for high level, what shotgun metagenomics is giving you is everything. And we can characterize all of those little fragments into which species and taxa they came from, as well as what potentially they're doing. So you're seeing who's there and what they're doing. Now I'm gonna flash a few little slides to talk a little bit about what the, the context of this is always, well, what to compare to, what do other things do? And this is a little bit of a history lesson as well. But let's, let's dive into kind of what this looks like. Awesome. Do you guys see my slides?
Maybe.
Cool. This is from our tech deck. Again, everyone should have access to this. We have a bio— we have a white paper as well that dives into all of this in much more written detail. So if you're really curious to dive into more, I highly, highly encourage you to check out both the deck as well as the recent white paper. But shotgun metagenomics, the reason why we're really such a big advocate of it and why it's the only technology we use here is because it presents a very complete picture. So other methodology, kind of the, the thing that started the metagenomics field was 16S. In this way, you're not looking at every piece of DNA. You're really just looking for particular fragments of a 16S gene. This is an rRNA gene that all bacteria have. And notice the stress here is on bacteria and not microbes in general. It's a gene that's specific to bacteria. And when you amplify it, you make a lot of copies of it and you count those copies to figure out what are the taxa that are in your sample. Now the problem here is, as you can kind of see in this picture, it gives a very blurry picture here. Yes, you are getting some high-level genera of what's present there. You can say, hey, Escherichia is here, but you can't say E. coli and you can't say E. coli strain, you know, XYZ, right? You can't get down to that level and you wouldn't be able to say what genes that E. coli had, which is really, really important. Bacteria like to share genes a lot. So when we see the species-level characterization, while that's really helpful, it's also really important to know what gene and what, capacity and potential this bacteria has for doing these functional roles. And so the shotgun metagenomics gives you that. It gives you not only a much more crisp, clear picture here, but all of the dots here are how we represent the function. So the bacteria, of course, these little, little like cockeye and like, you know, little, little dots there. 16S is giving a blurred picture. The shotgun metagenomics is giving all of the species as well as all of those functions that are doing as well. So it gives you a very complete picture, very able to kind of dive into not just who's there, but the mechanistic roles that they're playing. Emily, anything to add before I go to kind of another technology?
I think, I think the, the clinical thing here is like, I mean, not just underline what you said about it's not only about who is in the gut, what species are there, it's about what functions can they carry out. And that is really important when you're thinking about supporting your patients.
Awesome. The other, the next kind of comparison I'll do here is to PCR tests. I'm gonna actually broaden this into two areas, PCR and culture-based tests. So these are things that you'll probably find relatively commonly on the market. Things like GI-MAP use this. It's, it's things that like have a very targeted panel. We are interested in looking at these particular species, these particular function. It's not a full level composition, right? So if you're thinking of a piece of the pie, shotgun metagenomics looks at everything that's there. Like I talked about, we, we cut up all the DNA that's in that sample. We looked at everything and all of the functional capacity there. PCR says, hey, there are these particular things that we know are really, really critically important, and we're going to really, really dive into that slice in, in great depth and ignore everything else. Maybe not ignore, but just not really capture it. And we think about microbiome health, we really think of it as a community structure. It's, it's important not just what bad things are there, do we see really low abundances of really critical things, but also what good guys are there and what roles they're playing. It's really hard to think of the gut microbiome as just what are kind of the presence, absence of really, really kind of like unfriendly taxa. If you're not thinking about what the short-chain fatty acid production is happening, what's— what they're doing for digestion, what cellulose breakdown you're seeing. So we think of this as often like it can be really, really helpful if you're really kind of focusing in on particular, particular things and only interested in those, but you're really missing out on the broader picture of what's happening here. Anything else that Emily said?
Yeah, I mean, I agree. I think, um, I talk about the environment, the microbial environment all day, and certain things thrive in certain environments, um, within, within the gut. And to support that, there's short-chain fatty acids, beneficial bacteria, there's so many different things. Um, and we wanna look at those functions too. And you're not gonna get that, um, with PCR. It's, it's a small piece of the picture.
Yep. And I wanna say here too, it is, it, it can be very, very specific. So it's like, it's like going for a, like, you know, it, it's like a magnet to some degree. So I will say if you have something at very, very low abundance and you're really, really specific to that particular target, it can be really useful. So we do have add-on qPCR tests. I will say for this reason we have an H. pylori and a Candida qPCR test that we add on additionally.. Now again, we still think shotgun metagenomics is the only way to view this entire community. But if you wanted to see if levels below our detection, below that shotgun detection limit that we have of 0.005%, that you might have some trace levels of these other, these other microbes in it, then the qPCR can go below that and say positive or negative at that level. So we do have those add-ons for those particular reasons. And again, thinking of like the value of PCR, it would be in those cases where something very specific, I wanna see if very, very low abundances are present. All right. Now the, the last technology comparison I'll do is to RNA sequencing. So RNA sequencing is probably, you'll, you'll encounter it in a few different other tests, but it's relatively rare. So now what I said was we specifically do DNA. DNA is, is very stable. Our collection method using desiccation can hold that DNA stable for up to 8 weeks as it travels, and we have no problems with it at room temperature. RNA, which is the transcribed DNA, is inherently very unstable. So when RNA sequencing— this can also be really, really useful and is used often in different science experiments and in different publications to really focus in on functions and what's happening in that particular time point. Usually when you're doing RNA sequencing in labs, there are very, very controlled experiments, right? So you're doing mouse studies where everything about that mice— those mice are highly, highly controlled, and you're maybe doing drug studies where you're giving a compound and then looking at the RNA spiking. For a lot of practical purposes, this is not very useful for shotgun metagenomics. In those cases, this RNA, which is very unstable, is often something that looks highly variable when comparing it over time. So if you take an RNA sample in the morning, it might look very different in the evening or very different after you've eaten a big meal, or if, you know, week to week it's highly variable based on all of these factors, which makes it very hard to interpret. The DNA and the shotgun sequencing is different. It's much more stable. While you will have variation in what, what functions these bacteria are producing at any given time, which is why we think of this as capacity, what can they potentially produce? What you're not gonna have that much variability in is the composition. The composition is relatively stable day to day. And if the same user samples the same sample again and again on the same day, the composition doesn't vary that much. What changes is over time. So week to week, month to month, as people interact with different supplements or different dietary changes, that's where you're gonna actually see that composition, that DNA changing over time as the community structure changes. So yes, there's day-to-day variation that we potentially aren't picking up at what these genes are actively expressing, but you're capturing the stability in the community. Sorry, that is very technical. Emily, do you have any thoughts there?
No, I mean, I think it's good. I think Viome is an example of one test that does use an mRNA technology. And I think, I think the stability is really important. And that gets into like a little bit more of our questions. But I wonder, Kim, if you— I'm going to tee one up here for you because I think you stepped right into it. Thinking about like that short-chain fatty acid capacity, production capacity, and those genes. And the stability of that potentially versus like stool chemistry when we see short-chain fatty acid actual production, what's physically coming out in stool?
Yeah, yeah, great question. And I mean, I want to, I'm gonna add a little teaser here ahead because we actually have a publication coming out for this very soon. We just got it back from review, so keep your eyes out. I'm really excited for what we're showing here. And I think it's, it's really, really, it's a really cool question to kind of talk about. So when we think about the shotgun metagenomics, again, we're looking at the gene capacity, we're looking at what genes are there, can the bacteria be doing it? And what we're not looking at is directly measuring those compounds. And this is really important for a couple different reasons, but it also could explain some variation that you might be seeing between tests. When you're looking at stool chemistry, which we do have our Pro test, which also includes some stool chemistry measurements as well, we're looking at the direct compounds that are the metabolites that are coming out of the stool as well. Now think about this for short-chain fatty acids. Short-chain fatty acids are something that are supposed to be absorbed by the body. So when short-chain fatty acids are produced by the bacteria from what your diet is, is so we have like fiber comes in, the bacteria break it down, they produce the short-chain fatty acids, your body absorbs it, and some proportion comes out in the stool. Now the general conclusion here is that what is coming out of the stool is a proxy for what's being produced in the gut, but that is not always the case. Some examples might be in areas where you have poor digestion, right? Where it's not actually getting absorbed. So maybe the bacteria are producing it, but it's actually being secreted and then undigested from in the gut, in which case it's not having an overabundance in stool, might not mean it's actually being— doing the things that it should be doing. So yes, we have stool chemistry as well. We often like to look at these with short-chain fatty acids. There are a lot of correlations here. We also include things that are much more of the host response as well. So potential inflammation markers. These are things that the bacteria aren't directly producing. But of course, it's a two-sided relationship, right? Bacteria do things that can cause inflammation and the host response, the human response is to have inflammation. So by pairing it with stool chemistry, we can look at both sides of those coins. If we're not looking at the shotgun metagenomics, we can't see what the bacteria are doing, which means we don't know if they're overproducing certain things, if they're digesting the, um, mucus membrane more than expected, if they're producing things like hexa-LPS or other toxins. We can't see that without the shotgun metagenomics. However, without the stool chemistry, we can't see if necessarily we're having an inflamed response. So we think of them as very much two sides of the coin. Emily, did I answer your question there?
Yeah, that's perfect. That's perfect. And the, and the stability, like the short-chain fatty acid production, like my understanding is that that can shift. Like if obviously if you had a very drastically different meal, like say you, you ate out, you, you stopped at fast food, you're having a, you're having a day versus, and you test it versus, you know, having this beautiful Mediterranean diet dinner, you know, you might have very different output, but the capacity, the shotgun metrics, for what the microbes are able to do may not shift as widely as those, that output.
Yep. 100% agree. And that's also when you take the ProTest, we also ship this cold chain. That's why it's really important to, to sample the appropriate quantity to freeze it and send it over in with the appropriate instructions because here it needs to get that lab really fast. We're worried, we're worried about stability. We don't want it to necessarily be, you know, the, the swab with shotgun metagenomics DNA is very stable. It desiccates the sample. Nothing is happening to your sample if it's sitting in a mailbox for a day or two as it gets picked up. That is not true with the shotgun medicine or with, sorry, with the stool chemistry with our pro markers. Those have to go to the lab immediately.
Yep, that is exactly right.
Thank you ladies.
Perfect. So just to kind of bring it all back, cause I know we jumped right into the technology questions really heavily. I want to make sure that if you just joined us, we have, our clinical and science team here to help support and understanding just some of the reasons why Tiny Health chose shotgun metagenomic sequencing when it came to the, the reasoning behind the technology options, because there are other technology options out there on the market when it comes to choosing a stool testing company that you want to utilize for your practice. So the 16S and the qPCR and the, uh, some of the end culture and some of those other options you know, might be available through other companies. And Kim just very eloquently explained why Tiny Health uses shotgun sequencing and why it's so important, given the potential of the microbiome. So hopefully that helped kind of put it into context for everybody. The— I wanna move forward with the question about sample size. We got a couple questions in the chat about it, and I know we've got it before. So let's talk a little bit about How much sample size is appropriate? Is, is the small sample size that we ask for in our sequencing swab, is that enough? Is it, is it going to be representative of the whole colon, the whole digestive tract? What are we looking at there?
Yeah.
Yeah, we get this question a lot and I think it's a lot from people are very used to sending in large quantity of stools for things like stool chemistry, like the, like the ProTest, like the GI Map. When you send in a, a large amount, it's often because they are taking it apart to little tests. Like when you're thinking about the culture-based or the stool chemistry-based, all of those have to go to individual tests. They need a lot of it because they're looking at a bunch of little targets individually. And so they need a lot of stool for it. All of our stool goes to a single test, which is that shotgun metagenomics. And really we only need a tiny amount of it. So actually our caution is often on oversampling than undersampling. As long as you get a small swipe of it, that is enough because there are 100 million bacteria. I'm gonna quote this, the slide here, per milligram of wet stool. So when you get a tiny little swab of it, you captured a full complete community within that that is reasonably representative of not just that whole stool, but also that, that whole colon, that whole GI tract area. And this has been shown in, and we, we see this very similar across days. So what we're showing here in this slide is Bray-Curtis dissimilarity. So this is saying how dissimilar a sample is with 1 being the most dissimilar they'll ever be and 0 being the same, the identical, no differences at all. When an individual samples the same stool from the same swab or from, you know, 2 swabs, same stool on the same day, we get really, really consistent sampling so that, that sample does not change over time over, over that single day, right? Depending on where you sampled on that stool. And this is not true if you look at say different users over the same day where we get wide variation. So what, what I wanna point out here is is that sampling, repeat sampling from the same stool really shows high consistency. And this is true not just from what we've shown, but there have been a lot of publications that show this as well, that there is really high similarity across a single swab regardless of where you're swabbing on that stool. And regardless of if it's, if it's even a rectal swab, shows really high, high consistency in sampling. So just kind of emphasizing again that, that single swab of that toilet paper or that stool is representative of, of the whole stool. And I've personally in, in prior labs done experiments where we've taken the entire stool, freeze-dried it, and then homogenized it and then compared that to a single swab. And it was, I, it was again not significantly different here. So while I know it's very easy to get caught up in the details of did I sample wrong, our, our sample and our technology is really designed to say no, that it's very hard to sample wrong. It's very hard to not have collected enough. And usually when it hits the lab, we have plenty of stool to build that full consistent report on. Now I think I'll, I'll, we'll pass a little bit to Emily here too, but a little bit of does it represent the entire GI tract? Now this is more of a complex question. So when we think of the microbiome, and while we do know that there are bacteria living across your GI tract in various ways, the, the biggest proportion of the microbiome, the most largest amount of your community is in that large intestine and colon. So when we're looking at it, and this often can swamp out anything else that's happening upstream of it because this is where the bacteria are really designed to, to survive and flourish and thrive. So this is the majority of your community, and it's possible for the small intestine or bacteria that are higher up to pass through to the large intestine and to be represented in that sample. When we look over time at, again, other studies that have done various methodology that allows them, often from biopsies, but to look higher up in the GI tract and specifically sample and say what is here, you'll often find community overlap. So there are changes by these areas, they're very environmentally different, we would expect the microbes that thrive in these different areas to change relatively dramatically, but you can often see high overlap. So if there's overabundances in certain areas upstream, they can carry through and be, and be represented in that that stool sample depending on how overabundant and what else is in your community. So complex question. Emily, anything to add there?
Yeah, no, I think, I, I think you did well. I think that the complexity is like thinking, thinking nose to tail, if nothing else, right? And the, these bacteria, obviously they're gonna be housed in the colon. It's where the microbiome is. And sometimes we can glean a little bit of information about like maybe digestive insufficiency or other things that might be happening upstream and, and why the population looks a certain way. But I think that's a, that's a great answer about the microbes themselves. And like, we're not necessarily sampling the small intestine itself. And I get that question clinically a lot of like, is this indicative of, of SIBO? Well, this is the large intestine and not the small. So I think, I think there's a lot of caveat to that.
Yeah, yeah, we definitely do get that, that question a lot. And the environment shifts quite dramatically, you know, throughout the entire GI tract. So it's very important to be aware of that. And we start to see clinical dysfunction when that does not happen. So that's what we want to see. I think—
all right, another thing kind of around this too that made me think of it, maybe this is the question that's coming up, but, um, also I think we often get this paired with, um, Did I contaminate my sample? Like really thinking about like what contamination is around or like, you know, that, and it's true when you open up that swab, bacteria are all around you. We just generally assume like even if you've just washed your hands as the instructions ask you to, that your hands have some bacteria on them. The sink, the water, all around you, there are some level of bacteria. What's really nice about our methodology and shotgun metagenomics in general is that we don't do any amplification. Now why is that important? If you're sampling a gut sample or even vaginal, there is a healthy large community in it. Which is gonna be much more bacteria present and microbes present than anywhere else around you. So even if you directly swabbed your skin or your sink, yes, there are some bacteria there, but compared to what's present in that stool, what you're gonna be seeing is just the stool. Thinking about like a microbe-rich community, all of that's going to overrepresent anything that if you got a little bit of skin sample or a little bit of, let's say, air sample or something particulate in that manner. We, I've previous work, I guess, in previous labs, I've been very active with the, environmental microbiome as well. Like, we tried to get stuff from air, we tried to get stuff from sinks and stool— or sorry, from sinks and counters. And it's hard because the— well, the bacteria are there, often you have to culture or amplify to really see what's there. So these represent a very, very, very tiny amount, if possible, contamination. So usually when we get questions coming in being like, I think I might have had it touch my skin alongside the toilet paper or something like that, usually we have very little concern here that there was a massive amount of bacteria that would've contaminated the sample. Now, the one thing that we have seen and that we highly caution against is toilet water. So if it is sampled, like, again, we don't recommend that you sample from the toilet water itself with, if the stool is in there, or if you get splashed on from toilet water, this water can actually carry a lot of bacteria in it. As you'd imagine, we don't think of toilets as clean places. And once you add that water contamination, it can bring in those water bugs.. So one of our QC steps is actually to really look very closely at these samples and see if we can see water contamination, or if someone reaches out and lets us know that there was potential water contamination, we can look for it as well and see if that's influencing the community. Again, high amounts of water bugs are present in this, and this is usually our red flag to be like, okay, was there potential contamination here? That would've been more than just like a brush of a dry skin or an accidental, like, you know, you were breathing on it as you were taking it out.
Exactly, yes. And that was, we did definitely get some questions submitted on that of what are the common errors that might need to be looked out for from a perspective of things like, yeah, touching other areas, not snapping the cap down appropriately, all those different questions.
Yes. Yep. And they, it uses desiccation again, really technical. I love to nerd out on this, but like the swab sample doesn't use a chemical compound or anything like that. To preserve your sample. So you don't have to worry about spilling it at all. It also means that like, if you don't, like, nothing's gonna spill out if you don't close the lid. Like, we want you to snap the lid, please pay attention to it. But it is something that like the, the sample will still desiccate and dry out. And that's the way we're preserving the community and why it happens so fast. So this is also why we tell you not to sample too much. If you sample too much, the swab has a hard time desiccating it. And that is the only time that we get, say, aerobic overgrowth. So higher amounts of Enterobacteraceae or E. coli can come through. If you way overload that sample and it can't dry out appropriately.
Mm-hmm. Yes. And as you mentioned before, it is really important if you're doing a pro kit with that separate sample that it is kept in that appropriate temperature-controlled environment and mailed quickly. So that can definitely influence the outcome of that test. All right, awesome. Thank you so much for jumping into that one, Kim. Let's move on to a question that we have about Functional gene quantification. So we've talked a little bit about, you know, what are the things to look out for? What are the different types of technology? Why did Tiny Health choose shotgun sequencing? And so let's dive into what is functional gene quantification and how does Tiny Health utilize that data to interpret the microbiome's potential for functions? What is, what is, what do functions even mean? In the microbiome.
Am I having fun on those? I'll just post it on this one while I kind of give an introduction to it. So yeah, like we mentioned before, one of the real, real values of using shotgun metagenomics is that you're not just seeing species here, you're not just seeing lists of names. Those can be really important, but we're actually seeing what they're doing. We're seeing the functional capacity that they have. And when we say that functional capacity, function, you could functional potential, what we mean is that we're looking at these genes of the bacteria and we're assigning them to what, what they specifically do. So we look for ones that have a really high importance in the gut microbiome and can let you know quantifiably where you sit in a, in a typical healthy range. So for example, one of the biggest things that come up often are short-chain fatty acids. For short-chain fatty acids, it's not just important that you have things that might produce short-chain fatty acids, like the Colibacterium is one of One of the great examples, everyone's usually looking, do I have to have the Colibacterium? I know this is a short-chain fatty acid producer. I know it is really important with butyrate. Well, the Colibacterium is actually highly variable, and those different strains have different capacities to produce, to produce short-chain fatty acids and butyrate. So what we look at instead is the actual genes for butyrate rather than guessing, is this a strain that does this or not? We can look at the genes and count up the genes and get an idea of what is your potential and capacity to produce these different metabolites. And then we put, present this in context with a healthy population. So if you have more genes, we don't know how active those genes are. And a lot of that depends on your diet. If you're not giving the appropriate prebiotics, then the bacteria can't be doing their job and producing those postbiotics. But if given the appropriate substrate, then they can produce these particular compounds is really what we try and get at with that functional capacity. And that's a lot of the report, especially when thinking about adult and adult health, the bacteria, the bacterial community, the microbial community is highly diverse. We see hundreds of different species and a lot of them are not well characterized, which means we don't know, is this actually a direct butyrate producer or not? So rather than again, guess maybe this is something good, maybe this is something just rare, maybe like, and unfortunately from the science here, there's a lot more characterization of bad things than good, which means when you're looking at these beneficial functions, it's just often those species are not very well characterized. So we take the guesswork out of it. We're not going to try and guess based on this long list of species whether or not they're producing these functions. We are going to look directly for those functions and then tell you where you sit. So sometimes when you have a lot of unknown taxa or not well-characterized taxa, this can be a good thing. And they're butyrate producers and they're short-chain fatty acid producers and they're digesting fiber, which is awesome. And so in that case, we're not like, you know, steering you away to get those unknowns out of your gut. On the flip side, sometimes you can have a lot of unknowns and they won't be actually doing those beneficial, those beneficial functions. So we'll be pointing out that as well, that, hey, it looks like you have a lot of things that we don't really know much about what they're specifically doing, but we know we're not seeing the genes that we want. And so let's think about ways of supporting that specifically.
Exactly. And I want to— so I have a couple of follow-up questions to that, but I, before I get back to you, Kim, I want to have— we had a specific question submitted, Emily, which was about how do you explain from a clinical perspective if you did like a pro-test, for example, how if genetic capacity, genetic potential of the microbiome is showing up for short-chain fatty acids, for example, as different than the actual measured amount of short-chain fatty acids that is in the stool, how would you approach that?
Yeah, I mean, I think Kim touched on that a little bit earlier. Mm-hmm. Um, but looking at the, the gene potential is really looking at the microbiome, um, and the community and what those microbes, um, have the ability to do. Um, again, that's, that's gonna depend on whether you're, you're giving it the substrate that it needs to carry out that function. In the stool chemistry, we're looking instead at what is physically coming out in the stool.. And, um, that differs, um, that can shift like meal to meal because we're not talking about community potential. We're, we're talking about what's actually being produced. Um, and it also, I think the stool chemistry side, I think of it as, um, we get more information about what the body might be doing, right? There might be inflammation at play, there might be digestive sufficiency at play. Um, enzymes, like things like that may be going on to influence this dual chemistry and what's actually happening versus the potential, which is really looking at balancing that microbial community.
Awesome. Thank you. Thank you. I just, I think it's nice to hear it in different ways.
Yeah. Yeah.
Because it's kind of a, it's kind of a complex thing to wrap your mind around.
So the, yeah. Can I, can I add to that just a little bit?
Yeah.
Because we've talked a lot about short-chain fatty acids and I think like we have all of these other digestive digestive capacity markers for like complex sugars and fiber and things like that. And a question I get often is, you know, why are you telling me to eat, um, gosh, cellulose when it says I have a low digestive capacity for cellulose? And, um, Kim, you can, you can kind of chime in here, but my answer is always like that, well, the population that carries the genes to help with that cellulose breakdown, um, it needs to grow. The population has dwindled, and, and what we need to do is feed it what it likes to grow the population and therefore have more genes for that function. And I think the catch-22 is that we're telling people they have low digestive capacity and to eat the food. Um, and so it's always a low and slow, like, don't eat all the food tomorrow, you might not feel great, you might bloat, right? Um, but slowly, let's increase the amount that we eat over time.
Yeah, a lot of that often comes— we think of to look at, look at your diversity or really your community diversity metrics as well can be really helpful here to understand, like, if you're, if you're low on diversity, we need to increase the pool there and, and hope to find some more bacteria that can produce these functions. And as you're adding in these fibers, we're, we're looking to kind of promote them. We're looking at like almost a natural selection environment in your gut as we're trying to really encourage those that can break it down to thrive more and giving them the environment that need. Often if you've had especially restrictive diets in the past or antibiotic use in the past, it can wipe out these different communities and then you need to bring them back in a healthy manner so that we can rebalance it. If they're, if they're not there, how do we introduce them and how do we drive that diversity and environment so that they can, they can get a foothold again?
Yep, you got it.
Awesome.
All right, we're gonna do our last like more technical question, then we're gonna get into some of the submitted questions, but I wanted to And some of this, some of the answer to this question was already said. And we, when Kim, you talked about our functional gene capacity that we look at on the test, but we had a question in the chat. Practitioner was wondering, how does Tiny Health shotgun sequencing stand out from other sequencing types of tests on the market in regards to maybe bioinformatics, how we develop our metrics? And then also Emily, if you wanted to comment on like, or age-specific metrics?
Yeah, yeah, I'll, I'll start with that first part of the question then about how do we stand out. So we have really invested on having a very rigorous comprehensive test that is, is validated across the entire bioinformatics pipeline. So other technologies, other tests often use shallower technologies, what I'll call them. This is kind of how we describe the 16S, um, or when we think about culture PCR-based, you're getting a blurry picture of the microbiome or a much smaller picture of what's actually important in the community. We think, and our approach here is to be comprehensive. We want the largest picture possible so we can best put it and give it in your hands for understanding it in the context of an individual and everything that's happening with them. So we sequence deeply, I would say probably medium depth. We get a broad picture of what's happening. We explore not just the taxa that are there, but we explore all of the functions that are there as well.. And we provide a— I know it's a lot of metrics for the first time looking at it, but it's a really comprehensive view of everything that's happening here and then prioritized in a manner that is very specific to the individual and then really kind of highlights what particular areas to act on across that microbiome to support it. So I think that's the, the broad high-level picture of what, what our technology is doing. And other technologies, often you're gonna get a much narrower picture. You're going to get a few things, often pathogens, I'll say, or unfriendly taxa. Maybe they're not actively pathogenic in that circumstance, but you're going to get like these particular flags. And often your thoughts are, well, maybe I need to give something antimicrobial to reduce this or focus on reducing like unfriendlies. And really you're not seeing the full picture of the beneficial. And how do we support the good there, not just try and remove the bad?
Yeah.
And to just piggyback on that, the environment, right? I told you I talk about the environment all day. So it is that like we can go after this disruptive or that disruptive and use antimicrobials. But if you're doing that, you're not looking at the environment that was a friendly place for that disruptive microbe to thrive. So then another one might step in and you're, you're kind of playing whack-a-mole with these because you haven't shifted that environment to be like more acidic or, or, you know, more creating more short-chain fatty acids, something so that it would be more friendly for the friendlies, the beneficials. Than for the unfriendlies. And then the age-related metrics, Shalise, about that question. So I think this is, this is something I love about Tiny Health is that we're, we're not only like using all this technology to really critically look at what's in the microbiome, we're also overlaying that with what we know about gut microbiome development. And so the infant gut we know is very, very different. It should be very low diversity., compared to the adult gut, which, which should have much more diversity. And so we do have these different reference ranges for, infants, um, toddlers and children, and then adults. And that's because of the different developmental stages, um, that we would expect to see in the gut microbiome. So to read a gut test, um, like say that you ran a gut test and there weren't different, um, reference ranges and you were trying to interpret what was going on with a 2-year-old. Via the reference ranges that are made for an adult, you really— it's not, it's not there for like the same development. It would be very different microbiome environments. So we do that. And I will say a caveat to that is our ProTest. So the stool chemistry portion of the test is only for 3 and above. And that's because I'm sure you've heard, especially the pediatricians here, the first 1,000 days of life being so important because we're, we're building that immune system from the gut microbiome. There's so much dynamically happening in the gut microbiome. And then around age 3 or a little bit after that, kids will have an adult profile microbiome. And that's when we can run a PRO test because we do not have those infant ranges for that test specifically.
Awesome. Thank you. That was going to be my next question. You read my mind.
I'm like, did you get that?
Love it. Okay, so thank you for that, ladies. Uh, we are— I think we very thoroughly went through the technology, the, the benefits, and why it is so, uh, clinically appropriate, you know, for practitioners who are looking to support their patients through microbiome, improving their microbiome health. Next, I have a couple submitted questions that were sent in, and then we'll dive into some questions that were submitted live. So these are A lot of these are more clinical, but I do have one for you as well, Kim. So the— we got a lot of questions, Emily, on just essentially what is the Tiny Health Test testing for? So we had questions like, does it test for H. pylori? Does it test for mold? Does it test for pathogens? Can you talk a little bit about what our practitioners are gonna see on a Tiny Health Test?
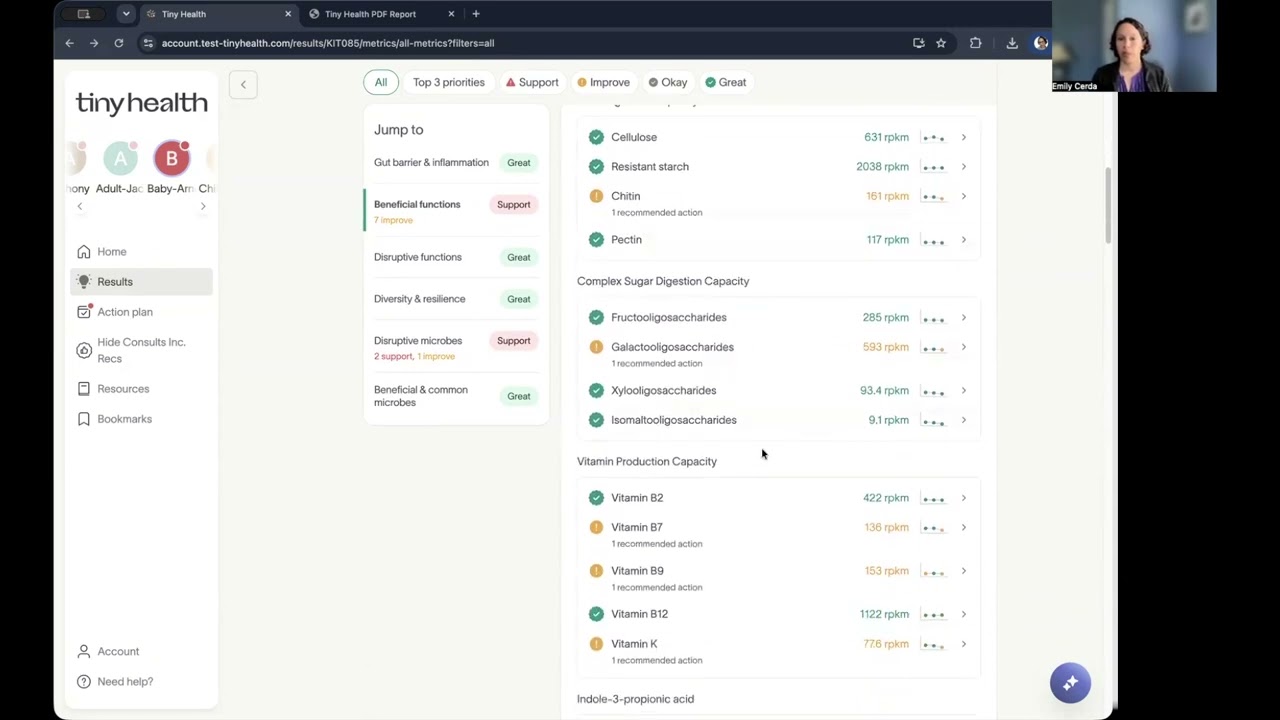
Yeah, so again, we're looking at that entire community. So then you get a picture of the entire environment. We list beneficials. So I will say that there's two portions of the test. So there's a portion where we're calling out metrics and we'll have beneficial bacteria, opportunistic pathogens, which are things like maybe an E. coli, H. pylori is in there, fungal is in there, some methanogens, and then some like amoeba-type parasites are in there as well.. We have inflammation metrics looking at kind of gut barrier, mucus degradation, hexa-LPS. Again, these functional metrics. So looking at the capacity of the microbiome to create short-chain fatty acids, to break down complex sugars, protein, fiber. I'm kind of mentally going through the test on my phone.
Yeah.
And we have a lot of like microbial enzyme and metabolites. So we're looking at also, um, the microbiome's ability to produce GABA, break it down, um, to produce beta-glucuronidase, um, gosh, uh, bile, uh, bile acid, um, yeah. So there are a lot, but then we also have a portion called the microbiome breakdown, and that we are just going to give you everything that is in your report. So where we talked before about like what differentiates us, we are not just reporting on those metrics that I listed, which are a lot. We're also going to give you the entire everything found from the topmost, like the biggest population all the way down to our sensitivity level, which is 0.005%.
Awesome. Yes, I know there's so much data in the test. It's really fun to dive into. I know.
I'm like, thinking through the list, then it's impossible. Yeah, come see me, I'd love to talk to you about it.
Yeah, we're happy to show you a test and walk you through it. The next question that I have is around— oh, there was a specific question about whether or not the test can show any markers for like histamine intolerance or burden. And we do have our recently updated with version 5, our histamine index, which is going to show not only species but also potential gene potential for histamine in the microbiome. So yes to that question. Uh, Kim, we had a question about hexa-LPS index. That comes up a lot. A lot of our practitioners, uh, you know, struggle with understanding that metric specifically. Could you maybe dive into that a little bit and how we maybe make those index metrics?
Yeah, and this is one that we recently revamped, so very excited to, to see the new updated version. If you're on version 5 reports, you'll be able to see this up there. We do have hexa-LPS on older reports as well, just using slightly different calculation strategy. So hexa-LPS is an endotoxin that's produced by bacteria, right? Specifically, often Enterobacteraceae are the culprits here. This is something that we, we know that like a lot of— there, there's different components of it. And so our index actually takes into account both the taxa that are there. So we know there are, there are some Enterobacteraceae that are particularly guilty of this, and we look for those specifically. Every single sample, we'll calculate, okay, how many of these different type bacteria are here? How do we know them by name? And then we also look at the genetic functional capacity as well. So we know what genes are important for hexa-LPS production. And so we tally up that portion as well. And this, this index and all of our indices, so we'll call a few different things an index, are looking at both of these together, looking at this combination of the taxa potential, the, the taxa capacity here, as well as the functional capacity, and then giving you an overall score for where you sit compared to the typical population of individuals who produce hexa-LPS. Now the, the value will have shifted. So before you were probably looking somewhere around like 10, 11, 12 if you were, if you were in the high range, and now the scale is from 0 to 100. But the important thing to really follow on here is the, the evaluation really. So if you were flagged borderline or high in the past, that is equivalent to being flagged borderline and high currently. And we've just made it a bit more sensitive to really pick up on those more rare cases of people who are probably having hexa-LPS production specifically because of a functional ability to produce it. Did that help?
Mm-hmm. Yes. Awesome.
Thank you so much. You'll see mucus degradation and our hydrogen sulfide also fit in this category.
Mm-hmm.
So they're ones that aren't just straight functional capacity counting genes. They're not just straight counting the taxa. They're a combination of both to give you the most comprehensive picture we can of what's happening with the hex LPS.
Yep. Excellent.
And the histamine index, like, like, yeah.
Yep. Histamine also fits into this category as well.
Yep. So, uh, there was a couple questions about some of the new updates to version 5 and some of the new metrics. If, uh, we won't have time to get into that today, but if you'd like to learn more about those, Emily covered them in depth in a previous Office Hours recording, so go ahead and check that out on our Practitioner Resources page, and you can learn all about our new metrics for version 5. If, uh, you've done a test recently, you would have gotten version 5 automatically, and the new metrics would be there. If you have an old test that you'd like to be upgraded to version 5 with no cost, then you can email practitioners@tinyhealth.com tinyhealth.com and we'd be happy to do that for you. But actually, email. Sorry, exactly. Sorry. Email hello@tinyhealth.com. Yeah, the patient has to send in the request. So if you have a— if it's your own test, then yes, we're happy to do that for you. If the patient was tested and wanted to upgrade to version 5, they need to send in an email to hello@tinyhealth to get their version 5 update. So sorry if that was confusing. Thanks, Christine.
Okay.
No problem. So let's get into a few submitted questions. We've got some time left and I want to make sure we get to the questions in the chat. So this was an interesting question. Um, practitioner said, I'm new to Tiny Health, familiar with BiomeFX and its science. They have us score the stool sample throughout the solid. If it "Is solid on my 2.5, 2.5-year-old child. The instructions said to wipe and then blot the collector and the stool on the paper. Do we know if that collects enough bacterial DNA of the microbes in the microbiome to get a full view of what is there?" Yes.
So I think this comes back to our initial question of does, does a small sample, is a small sample enough? And the, the answer really is is, is yes. From, from the validation that we've done internally as well as from a number of publications that I flashed a little bit earlier, we, we find really high consistency from even just a tiny amount of sample. Often if you can even see just a little bit of color on that stool from, from the sample collection, it is enough to get that, that full community.
Excellent. Thanks, Kim. This question is, I think, more for you, Emily. Kind of ties into the concept of retesting. So we can talk a little bit about frequency and what we recommend. This question says, 'Cause shotgun metagenomics is more stable, does that mean test results are considered actionable for longer? qPCR testing is considered valid for 3 to 6 months. Is Tiny Health considered valid for longer?
If so, does that impact the necessity to retest?' Ooh, I think that's a, that's a complex question because it depends on what happens in those 3 to 6 months, right? Like if somebody were to get ill and need antibiotics, obviously that can community could shift quite a bit. If you needed to go on a therapeutic diet that was restricted, that community could shift quite a bit. In general, again, I'm gonna lump this back to the age, how we have age-related metrics and different reference ranges. For infants, we typically see that it'll take like 3 to 4 weeks for that microbiome to shift, sometimes even 2 to 3 weeks if they're below 6 months. Um, for toddlers, it is more in like the 6 to 8 week range. Um, children and adults, because children will have that adult profile microbiome after 3, um, it is more like 3 to 4 months. So that's usually the retesting window that we're using. Now, I think this also gets complex because I have had, um, practitioners come and we talk we talk through the interpretation, and maybe there's a lot to do in a gut. Like, maybe there, there needs to be a little antimicrobial, a little, um, support of the beneficial bacteria, but then we also need to make some pretty big diet changes. And so I think that, you know, there's a few different ways to approach that. Some practitioners want to, uh, support the beneficials and, and use the antimicrobial and then check in to see if that did what it needed to do, and they know that they're still going to have to make, like, maybe increase fiber or, you know, work on that cellulose or whatever came through in the capacity metric. And so then they know that those are still things to do. And then there's others who want to do it all. They want to do the antimicrobial and they want to, like, work on the beneficials, and then they'll start to work on the diet. But it's slow, right? Because patients aren't— none of us are changing diet overnight. And so then that'll extend that a little bit. So I do think it is actionable over a good long period of time, provided that another variable doesn't enter, like antibiotics or restricted diet or, you know, illness, GI illness, something like that. Yes. Stress. Who's stressed?
Yeah. No, not me. No.
Yeah, yes, exactly. There's so many things that can impact the microbiome, and we never want to overlook the influence of the environment, right? So, and that actually kind of ties into this next question here. This practitioner said, I had a couple clients who took a very small sample, test did not provide any significant findings. Child has been having significant constipation issues, was surprised, especially Since usually there are some findings that I will see in this type of situation, could that be a sampling issue or have you seen this before? I need to explore further what's going on.
Yeah, for, for constipation, I mean, I think it's hard to talk about it without seeing the kit in front of me. I'd love to see like how is the beneficial bacteria. I'd love to know how is fiber intake. Are we making good short-chain fatty acids, is there any inflammation. Um, and I'm gonna, I'm gonna shift this a little bit to like my own experiences. I've had a lot of practitioners come in, um, eczema is a good example. We can use constipation as well, but say that the patient is exhibiting like that they are just covered in eczema and microbiome looks beautiful and my response to that is always like, okay, well, we can support the microbiome a little bit, but it also gives information that maybe this isn't stemming from the microbiome and we need to shift to maybe immune support, or we need to check out, you know, some, some other— like, it's very complex. There's many, many systems that are involved in constipation or eczema, for example.
Yep. Yeah, I think that's, that's a great response, and I think that's that's, uh, we, we definitely think of gut microbiome as a piece of the puzzle, and for a lot of people it's a very significant piece of that puzzle. And so the testing in itself can be a way of just making sure, like, where are the imbalances there. On individuals that have really healthy-looking guts, it's nice to at least be able to have maybe checked off that box or consider it as, you know, you're trying other methodology to, to work on symptoms and making sure you have a baseline here of where you want to go back to.
Mhm, exactly. Absolutely. We love talking about the gut microbiome and is that, that is our jam over here at Tiny Health, but there are other influences on the body. And so it's always great to start with the gut cuz it's the foundation, but there are sometimes situations where it's not the main contributor, you know, to the patient symptom presentation.
So yeah, I think I will point out too, we do have a condition association place.
Yeah.
Um, in our app.
So you're welcome to, again, if chronic the patient is the main reason concern that you're interested in, you're interested in what metrics are typically flagged or often, often high in these situations, it's a great place to start. So in that case, maybe there's not a lot of things flagged, but you can look specifically at what are often flagged in this condition and is it something that matches up with, um, what you'd expect to see.
Exactly. Also, I would recommend booking a call with one of our microbiome specialists to go through the test because there could be some things that are borderline that could be improved and or optimized, right? Just because things are okay in the reference range doesn't always mean that the patient is asymptomatic. So, or not presenting with some sort of level of health challenges and they might need more optimization support versus, oh, we have a bunch of reds and oranges and yellows on this test. So, uh, we have like some very obvious things to influence, whereas a microbiome specialist who's looked at, you know, hundreds of tests might be able to point out some of those things that could help. All right, well, we are right on time, ladies.
Amazing. First time for everything, right?
I know, right? Um, I wanted to just thank everybody for being here today. I truly appreciate your time, and we got some fantastic nuggets of information, and it was so great to just learn about why Tiny Health uses the type of technology that we do and why it's so clinically important for our practitioners to understand that. And when they're looking at the tests and the metrics, so thank you for being here. And we will have next month for July, we have another office hours. We're always on the second Wednesday of every month. So you can keep an eye out on your email to register for that. I believe next month we're doing action plan, right, Emily?
I believe so.
Yeah. Yeah. So today we got a really deep dive into the technology of Tiny Health, and it was such a pleasure to have Kim here to hang out with us and nerd out today. And so next month, Emily and I are going to be doing kind of a similar format. It'll be a little bit less presentation-y. It'll be more conversational in regards to how to approach the action plan in the Tiny Health Test and turn it into a, you know, a care plan for your patient and how you want to approach that, how you might want to customize it, things to keep in mind. Um, because we do get lots of questions about, you know, what's the best way to prioritize the action plan? How can I make sure that is appropriate for my patient? So we're going to be answering all those fun action plan questions next time. And if you submitted a question that didn't get answered today, uh, we do appreciate all these fantastic questions you've got, and we're going to hopefully be able to answer some of them, your more clinical questions, next time in next month's Office Hours. So stay tuned for that. Thank you, everybody. Have a wonderful—
thanks, Kim.
Thank you.
Rest of your day. Yeah, and we will see you all in a month. Yes, second Wednesday of the month. You got it, April. And then please do, uh, use our discount code if you haven't ordered a test with us before and schedule a call with one of our account specialists. If you've already ordered a test and you want to schedule a clinical review with one of our clinical team members to review it, you just go into your practitioner portal, click the book a call button at the top. It'll take you to our Calendly page where you can then select a specialist to go through the test with you. If it's your first test, you want to book the 60-minute call because it's pretty in-depth. There's a lot to go through, uh, so make sure you do that. Don't book the 30-minute. That's a mistake.
Everybody regrets it.
So yes, but we are happy to go through that with you, and we're always available to you. Your, our, your clinical support team is here to support you in whatever capacity you need, um, to learn how to interpret these tests the most appropriately for your patients. So thank you everybody, and we will see you then. Have a good rest of your week. Bye!
More from Tiny


Tiny Health Raises $33M Series B to Establish Microbiome Intelligence as the Standard of Care