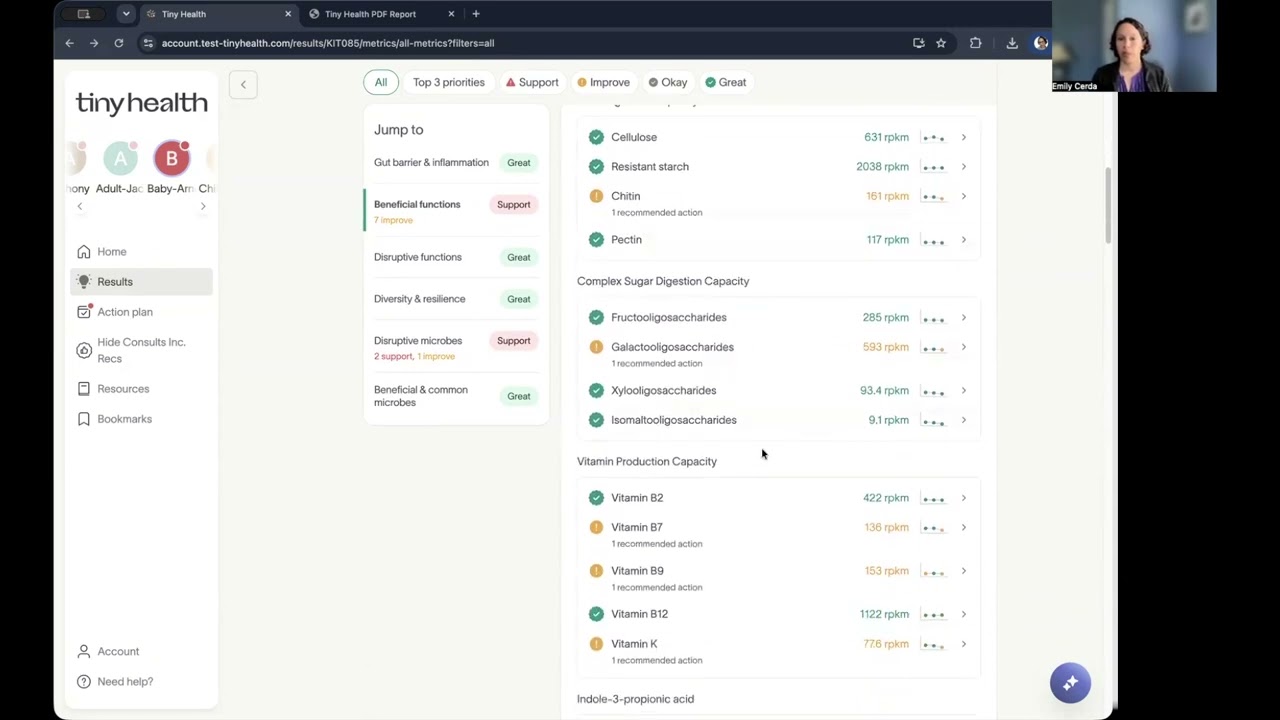
A practitioner-oriented walkthrough of Tiny Health’s Pro kit results by microbiome specialist Emily Serda. Covers that Pro markers are stool chemistry measures (distinct from shotgun metagenomics), and explains key metric groups: inflammation markers (secretory IgA, calprotectin, lactoferrin, lysozyme), digestion/absorption markers (pancreatic elastase, fecal fats, carbohydrate residues), short‑chain fatty acids (concentration vs percent), intestinal health markers (occult blood, pH, color/consistency), and beta‑glucuronidase (detoxification/estrogen recycling). Includes clinical interpretation notes, retesting/referral guidance, and recommendation to pair Pro outputs with shotgun gene-capacity data and patient presentation.
Questions this video answers
200 and above is normal.
Chapters
Hi, I'm Emily Serda, I'm a microbiome specialist here with Tiny Health. I am going to go through a pro kit today and walk through what each of those metrics means. If you'd like a general overview to our Tiny Health test, then you can go into your practitioner resources and we do have a practitioner walkthrough of the entire test to kind of orient you. So here we can see. This is a pro test for a 64 year old patient. I'm going to click into See all metrics and at the very top of our results we're going to see the Pro practitioner markers. Pro markers are stool chemistry markers. So these are different than the shotgun metrics that you're going to have in the rest of the test, the shotgun metagenomics testing, it is whole genome testing and it is looking at the microbes present in the gut as well as the genes present that are able to do functional actions. So if the microbe, if the microbiome doesn't have the microbes, that's one thing. If it doesn't have the genes, then it can't perform a function. So here in the pro test we are looking strictly at stool chemistry and this is like what's coming out in the stool. So here at the top of the promarkers you'll see four inflammation markers. We do have secretory IgA. This is looking at immune response in the gut. And this one, it can be driven high with acute information inflammation and it can be driven low typical to like a cortisol response where cortisol is high acutely but over time kind of becomes depleted and then is low and more of a chronic situation. The secretory iga, it can be driven by microbial inflammation, but also this can be an exogenous source or an outside trigger, like a food reaction in something in the environment, something that is triggering immune inflammation in that gut. So then we have calprotectin and lactoferrin and I'll kind of talk about these together. Both of these are pretty strong indicators that are related to IBD specifically. So calprotectin, it is used as a pretty sensitive marker for ibd, whether there is a flare that's current even during IBD treatment, or if this is something that has gone undiagnosed and needs to be caught. So we do take this pretty seriously for any of these markers. When you're looking at them, you're obviously going to see what, what the range looks like, but you're also going to be able to come down to the about section and learn a little bit more about this. So both calprotectin and lactoferrin, very important markers of inflammation. They can usually when these are elevated, we're maybe retesting in another four to six weeks. And if they remain elevated then often that can be a referral to a specialist for an endoscopy, make sure that there's nothing big going on there. For lactoferrin specifically infants, we don't usually recommend this being run for infants, but if that were to happen, lactoferrin we would expect to be high in infants because of its present presence in breast milk. So lysozyme, this is a non specific marker of inflammation. So this is related more to neutrophil action. And this one, sometimes when this is out of range, this is related to a picture of dysbiosis, microbially driven inflammation. So often, especially when the picture of inflammation overall looks like everything's normal, but lysozyme is high. It's also worth noting this is innate response can occur with a GI infection, virus, something like that. So the lysozyme tends to stay elevated. I believe it's four to six weeks after a GI illness. So we want to rule that out as well. Okay. Further down in the promarkers we can get into digestion and absorption markers. So we are looking at pancreatic elastase production. This is what's coming out in stool. And 200 and above is normal for our test. Below that we start to get into considerations about pancreatic or pancreatic insufficiency. Okay. Fecal fats will be reported on. This is a fat stain to tell you if there are fats steatorrhea occurring with your patient. The muscle fibers and the vegetable fibers, these actually they are on some of our older reports and, and they're no longer on some of our newer reports because we're finding that we have enough without those specific markers. So those a lot of times these are related more to chewing and being mindful and maybe, maybe some digestive enzyme needs. But carbohydrates on the other hand, when this is positive, it means that there's some sugars coming into that stool and that can be looking at definitely looking at diet quality and balance, but also thinking in terms of digestive enzymes. And do we need an amylase or something to help break that down? Okay. Further down we do have pro short chain fatty acid production. So this is again what's physically coming out in stool. And here we can see you'll get a Range, telling you if there's kind of the optimal range of these short chain fatty acids. And in the sample, a lot of times with these, when they're trending high, that could be representative of a great diet, really high in fiber. We're making a lot of short chain fatty acids. You really have to pair this with patient presentation. And I like to pair this also with the shotgun markers for short chain fatty acid capacity. Because in the shotgun test you're going to get the genes in the microbiome and how many are there to help with that function. And then here you're getting, with, you're getting the output. So what's actually happening? A lot of times pairing those together can give you a lot more information about your patient. But from a patient presentation standpoint, this could be great diet. This could also be a situation where we have a lot of inflammation in the gut with high output. And so we're not having as much absorption of those short chain fatty acids as we would like. So there's a lot coming out in the stool. Low markers, on the other hand, would probably signal to me that there's either low beneficial bacteria that will help to create the short chain fatty acids or that perhaps there's low fiber intake for the patient because that has to, that has to occur alongside those beneficial bacteria in order to create those short chain fatty acids. To start with the propionate here we can see this one is out of range. So this would be an interesting one to look into. Again, you can look into the about section to learn about these. One thing I will note here, concentration is how much butyrate is in the sample, whereas butyrate percent is looking at it relative to the other short chain fatty acids that are there. Okay. Down further intestinal health markers, we are looking at occult blood to see if that's present ph to see if we have an alkaline or an acidic environment. Things that can influence this would be a loose stool. A loose stool would have a quicker transit time through the GI and with that we would expect to see a lower phase. There can also be microbial inputs to drive the ph, either high or low. Color and consistency are also noted here just so that you have that information. Again, if this said consistency and it said loose watery and we saw a very low ph, that might explain that metric. The last thing in PRO enzymes is beta glucuronidase activity. So here we do see how much beta glucuronidase is coming out in stool and this beta glucuronidase it is related to recycling when it's high, recycling medication, certain medications, toxins, even hormones like estrogen. And so working on kind of phase two detoxification pathways and support with liver and that for high beta glucuronidase. Now, low beta glucuronidase I see occasionally. And this can occur if somebody's eating like a really great vegetarian diet, strict vegan diet, so they're not getting a lot of protein and fats, like animal protein and fats in their diet. That low beta glucuronidase can also occur when we need liver support. So interestingly enough, the. The free components to create the beta glucuronidase, they will get stuck kind of in a stagnant liver situation, and then they're not free. And if they're not free, they're not able to bind to create beta glucuronidase. So then we'll see a low result. So thinking, I think, phase two detox support, whether this is low or high, and also thinking about this in terms of estrogen. So if estrogen is high, then the body may ramp down beta glucuronidase production as a result. And so we might see a low beta glucuronidase opposite of that. We can also see that a low estrogen situation may ramp up beta glucuronidase activity. And you have the complexity of beta glucuronidase recycling these things when it does get high. So definitely you have to take this and pair it with your patient presentation to try to figure out your. Your protocol moving forward. But that's a general overview of the pro results and how they're going to differ from the shotgun results, which are further down. I hope this has been helpful.